While I swiftly learned to never compare your PhD life and schedule with other PhD students…a year into my PhD presents a great opportunity to highlight what a day in the life looks like for me, and how it may be so different to others.
Currently, my days largely revolve around data collection for the second study in my PhD. This study is looking at gut hormone responses to each macronutrient in older adults with low appetite.
7:15am – Alarm:
The day begins with putting to use all that nutrition knowledge…PB & J on toast followed by a short cycle to the lab (more often than not in a coastal headwind!).
8:00am – Prep time:
My data collection involves many different elements, meaning there is plenty of preparation needed for each testing day. This includes things like making sure I have the appropriate phlebotomy equipment ready, the centrifuge is cooled and the necessary meals are prepped for the day.
8:30am – Participant arrival:
As soon as participants arrive, I check their study eligibility and pop a cannula in their arm, to allow me to take regular blood samples throughout the day. After this, we take the first blood sample and record their subjective appetite. Participants are then faced with a macronutrient breakfast of either 100% fat, protein or carbohydrate (not as bad as it sounds!).
8:45am – Experimental block begins:
Over the next four hours I monitor the participants’ appetite, alongside taking regular blood samples. In the final hour of this block, I head to the kitchen to prepare the unlimited pasta meal!
12:45pm – Unlimited pasta time:
At the four-hour point we take the final blood sample and appetite measure and remove the cannula. We then provide an unlimited pasta meal to measure a participants energy intake in response to the macronutrient breakfast. Once complete, this marks the end of their testing visit, and they are free to leave.
1:00pm – Clean up and data storage:
Once the participant has left, I then clean down the lab and make sure all data has been recorded for the day. Storing the blood samples in the -80ºC freezer marks the final task for data collection.
1:45pm – Lunch and afternoon tasks:
The beauty of the methods I use in data collection is that I now have the afternoon to complete other tasks related to my PhD. These tasks can include things like enrolment visits for prospective participants, catching up on writing or assisting with the athlete consultancy service we run. This routine is also great as I can plan my remaining tasks around an afternoon swim, run or gym session.
4:00/5:00pm – Day complete:
Around this time, I’ll be making my way home. This routine provides a great work-life balance and allows me to carry on doing the things I love outside of my studies.
And that’s a typical day in the life for me! While testing days can be intense, the flexibility my PhD provides me allows me to balance my studies with other interests, making the PhD journey feel sustainable and rewarding.
For many people recovering from stroke, physically repeating a movement hundreds of times can be difficult or, in some cases, impossible. But physical movement is not the only way that we can engage the brain systems involved in movement.
We can also rehearse actions mentally, without physically performing the movement.
Mental practice has been studied in stroke rehabilitation for several decades and is now recommended within stroke rehabilitation guidance in the UK and internationally (Lin et al., 2025).
The 2023 National Clinical Guideline for Stroke for the UK and Ireland, for example, recommends that people with stroke who are able and motivated to participate in mental practice should be offered training and encouraged to use it alongside their usual therapy.
So, the question is no longer “Should we use mental practice?”
Instead, clinicians are asking “How can I deliver mental practice effectively in my stroke care pathway?”
Yet there remains surprisingly little practical guidance to help clinicians answer this question.
When we think about mentally practising a movement, we might immediately think of motor imagery: imagining ourselves performing an action without physically moving.
But there are other ways of mentally rehearsing movement too.
Watching a movement provides the brain with a rich source of visual information about what the movement should look like, and this can also activate the observer’s motor system (Binks et al., 2025). Imagining the same movement requires the person to generate much more of that representation internally themselves.
Following a stroke, that distinction can matter enormously.
Stroke can affect vision, attention, memory, executive function, perception and the ability to generate or manipulate mental images, alongside its more obvious effects on movement. A mental practice technique that works well for one patient may therefore be difficult or inappropriate for another.
This problem has led us to develop the Mental Practice Variants (MPV) Model.
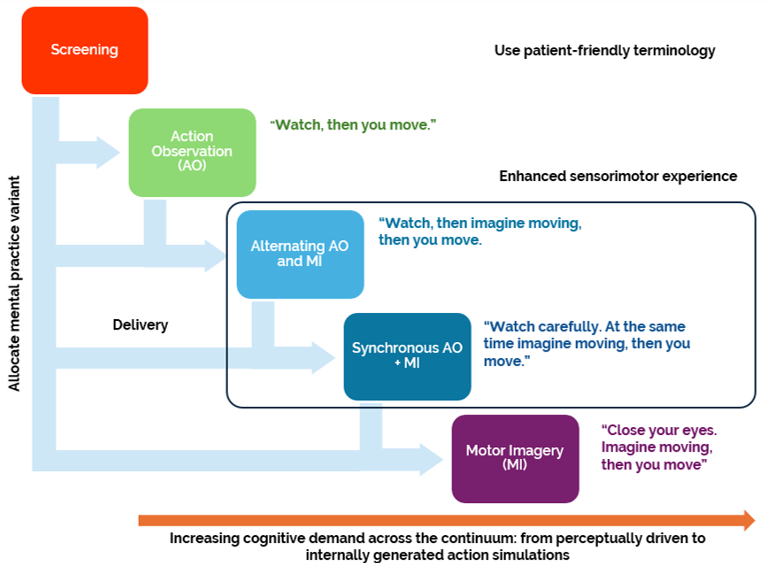
Rather than treating mental practice as a single intervention, our model distinguishes four related ways of mentally rehearsing movement:
→ Action Observation
→ Alternating between Action Observation + Motor Imagery
→ Synchronous Action Observation + Motor Imagery
→ Motor Imagery
Across these variants, the emphasis shifts from externally provided visual information towards increasingly internally generated representations of movement, and this is associated with increases in cognitive demand.
Instead of asking whether a patient can or cannot do mental practice, we can now ask which form of mental practice is most appropriate for that patient, at that point in their recovery.
Closing the gap between guidelines and practice
If mental practice is to fulfil the potential reflected in stroke rehabilitation guidelines, clinicians need practical ways of translating guideline recommendations into individualised treatment.
Our recent work at Newcastle University has therefore focused increasingly on this translation (Lin et al., 2026).
Alongside developing the MPV model from the scientific literature, we have been working with healthcare professionals involved in stroke rehabilitation to understand the practical questions that arise when mental practice moves from a research paper into a clinical setting.
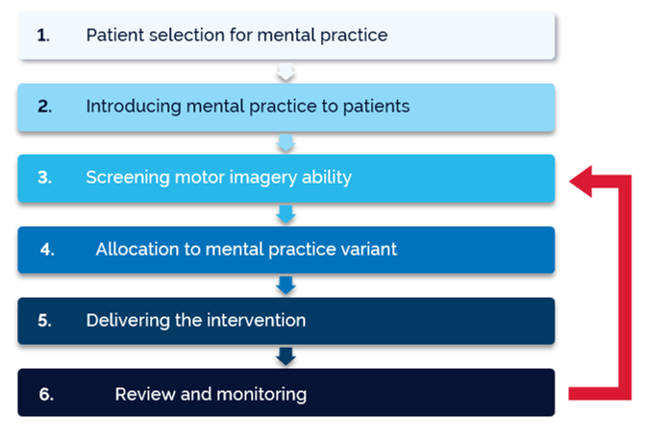
This has led us to develop a six-step framework covering patient selection, introducing mental practice, screening, allocation to an appropriate variant, delivery, and ongoing review and monitoring.
The aim is not to replace clinical judgement with an algorithm. Quite the opposite. It is to give clinicians a clearer framework within which that judgement can be applied.
A patient may begin with one form of mental practice and later move towards another. Another patient may remain with the approach that is most accessible and useful to them. Patient preference, cognitive and perceptual abilities, movement goals and response to the intervention can all inform those decisions.
In this sense, mental practice becomes less about prescribing a single technique and more about having a toolkit of related approaches that can be matched to the individual.
From knowing we should, to knowing how
This autumn, we are taking another step towards addressing this implementation gap through a new Newcastle University continuing professional development course for healthcare professionals working in stroke rehabilitation.
The course has been co-designed with NHS staff and will introduce the Mental Practice Variants Model and provide practical experience of selecting, delivering, adapting and progressing different mental practice approaches.
The course will initially be delivered face-to-face, with online provision also being developed to make the training more widely accessible.
From our perspective, putting mental practice into guidelines is only part of the job. The next step is making it easier to put it into practice, so that it can ultimately benefit patients.
To support this work, we are also preparing to launch a new Newcastle University supported website, which will act as the first online hub for a wide range of mental practice materials and how to resources.
J. A. Binks, R.P.W. Kenny, P. van Schaik, C. J. Wilson, D. Lin, T. J. Binks & D. L. Eaves (13 Nov 2025): The effects of combined action observation and motor imagery (AO + MI) practice on motor learning: a systematic review, International Review of Sport and Exercise Psychology, DOI: 10.1080/1750984X.2025.2575511
Lin D, Eaves DL, Gibbons T, Aquino MRJ, Edwards MG, Poliakoff E, Bek J, & Emerson JR (2026). Perspectives of stroke survivors and informal caregivers on home-based mental practice for upper limb recovery after stroke: a qualitative co-design study, Neuropsychological Rehabilitation, 36:6, 1122-1161, DOI: 10.1080/09602011.2025.2577376
Lin D, Eaves DL, Franklin JD, Robinson JR, Binks JA and Emerson JR (2025). Combined action observation and motor imagery practice for upper limb recovery following stroke: a systematic review and meta-analysis. Frontiers in Neurology. 16:1567421. doi: 10.3389/fneur.2025.1567421
Working in the Human Nutrition & Exercise Research Centre (HNERC), it might be assumed that nutrition and exercise are two things I have completely mastered. The truth is, that (presumably) unlike many of my colleagues, these are things I continue to struggle with.
Exercise for instance; whilst I love being physically active, going on long dog walks, being outdoors in the fresh air, exercise itself – the planned structured part such as going to the gym – is something I have a long and complicated relationship with.
On the surface, it seems simple: ‘move more’ and ‘just do it’. But for me, it rarely feels that straightforward. My brain has an impressive ability to overthink every decision. I weigh up the pros and cons, wonder how difficult it will be, whether it will fit into my routine (and my dog’s!), whether I’ll enjoy it, and whether I’ll still be doing it in six months’ time. I’ve spent hours researching gyms, comparing exercise classes, and creating carefully thought-out plans.
Sometimes those plans work—for a while. Then life happens. I get injured, work gets busier, the gym membership no longer feels affordable, or routines in the house change. Suddenly I’m back to where I started, asking the same questions: What should I do? Where should I do it? When and how will I fit it in?
It really shouldn’t feel this difficult, but for the most part it does.
So, why do I spend so long trying to establish a more consistent relationship with exercise and why do I spend a large part of my time researching physical activity and exercise?
The answer is that ‘exercise is medicine’; it has enormous potential to improve long-term health, reduce the risk of future illness, and enhance quality of life.
The importance of physical activity and exercise became particularly clear to me when carrying out research into the survivorship of childhood and adolescent cancer here at Newcastle University and in collaboration with PanCare (a European society and charity for childhood cancer survivors). Through this work, I learnt about the long-term effects of cancer treatment – often called late effects – which are health conditions that can develop months or even years after the cancer treatment has finished. For example, some chemotherapy treatments, called anthracyclines can increase the young person’s risk of heart problems later in life. Physical activity and exercise have been identified as a key strategy which could help these young people protect and maintain their heart health (among lots of other benefits) but research indicates that the majority of these young people are insufficiently active.
Feeling strongly that these young people should be supported to look after their health, led to a project called BEACON1 (BEing Active after ChildhOod CaNcer) in which we reviewed existing evidence,2 and spoke to survivors of childhood cancer aged 10-24 years old about physical activity, with the aim of specifically identifying what helps and hinders them to be active and understanding what support could help them to be active in their everyday lives.
Likewise for a project I am currently working on with women who have had breast cancer (PURE-EX),3 there is a lot of evidence supporting the role physical activity and exercise can play in reducing the risk of the cancer returning and improving survival and other important health outcomes such as emotional wellbeing and fatigue. But again, we know this is a group who struggle to be active.
So, if we know the value that physical activity and exercise can offer people in general, and those who have been treated for cancer, what is the issue? Well, part of the issue lies with one common misconception: that knowledge alone will change behaviour.
That is something I have learnt not only personally, but also professionally through studying health psychology. Health psychology explores how biological, psychological and social factors influence health and illness and can help us to answer the question: if we know something is good for us, why is it often so difficult for us to actually do?
We all face barriers when it comes to adopting important health behaviours such as exercise, and good dietary habits (and hopefully avoiding/giving up harmful health behaviours like smoking and vaping), and those barriers deserve understanding rather than judgement. Although human behaviour seems like it should be something what we should be able to understand with ease, some people state that rocket science is in fact easier to understand.4 Whilst rockets follow clear laws from maths and physics which allow us to predict what should happen each time, human behaviour results from a whole array of influences (e.g., beliefs, emotions, past experiences, the people and environments around us, culture and society) which makes it extremely complex and at times, unpredictable.
And when an illness like cancer is involved, it can throw up even more challenges. Muscles become weaker, new aches and pains appear, and energy levels fall with fatigue often becoming an ongoing struggle. At the same time, people are often adjusting psychologically, emotionally and socially to the trauma of cancer. Many describe feeling as though they are living in a body they no longer fully recognise, trust or feel comfortable in. They are often unsure of what they are now capable of doing, and whether it is safe or not. Starting—or restarting—physical activity in that context is about much more than just knowledge.
Whilst research can often focus on generating evidence about what people should do, my work is about understanding how we can support people to do it in ways that acknowledge the challenges they face and ultimately help them live well after cancer. For both the BEACON and PURE-EX projects we hope our work will result in better support and real change for patients, helping them to feel encouraged and able to be physically active and exercise in a way which will be sustainable and which will help them to feel better mentally and physically.
I’m excited to continue that work here at HNERC, alongside colleagues who share a passion for improving health through research. And who knows—perhaps by helping others overcome barriers to exercise, I’ll become a little better at overcoming my own.
References
Brown MC, Araújo-Soares V, Skinner R, Glaser AW, Sarwar N, Saxton JM, Montague K, Hall J, Burns O, Sharp L. Using qualitative and co-design methods to inform the development of an intervention to support and improve physical activity in childhood cancer survivors: a study protocol for BEing Active after ChildhOod caNcer (BEACON). BMJ Open. 2020 Dec 21;10(12):e041073. doi: 10.1136/bmjopen-2020-041073. PMID: 33371034; PMCID: PMC7754664.
Brown MC, Podmore M, Araújo-Soares V, Skinner R, Sharp L. Childhood cancer survivors’ perceptions of the barriers and facilitators to physical activity: a systematic review and thematic synthesis of qualitative evidence using the theoretical domains framework. Health Psychol Rev. 2023 Jun;17(2):277-300. doi: 10.1080/17437199.2022.2032795. Epub 2022 Feb 14. PMID: 35081866.
Orange ST, Brown MC, Hallsworth K et al. Co-development of a programme to improve physical activity support for women after breast cancer treatment: a pre-protocol for PURE-EX [version 1; peer review: 1 approved with reservations]. NIHR Open Res 2025, 5:3 (https://doi.org/10.3310/nihropenres.13773.1)
Sarvadi, P. Human behaviour would be easier if it was rocket science. Accessed 30 July 2026 from https://www.forbes.com/sites/forbesbooksauthors/2019/11/13/human-behavior-would-be-easier-if-it-was-rocket-science/?sh=2fde0d6557cb.
In July the HNERC and Newcastle University will host the Nutrition Society annual congress. This is the largest gathering of nutrition and allied sciences in the UK annually. It marks a departure from the society’s historic conference format (which aimed at its own members) and now seeks to draw the wider community of scientists and practitioners together at a single event. It is a considerable honour to be invited to plan and to host this event, and I have worked closely with HNERC alumnus Amelia Lake as co-organisers. In this very late stage of preparation (I write this a matter of weeks before the congress) most of the arrangements have been locked in, the programme is decided, exhibitors primed and ready and the last delegates are registering. We can’t wait to get going.
The organisation of such a large event is complex and needs a large team around it to deliver. Amelia and I worked closely to develop the core programme of Nutrition Society symposia that anchor the event. We have consciously tried to shape a programme that has something for everyone, from laboratory-based nutritional biochemists through to community-based public health researchers. We built on the distinctive and complementary network capital of each other to deliver the programme. In turn the society’s staff led on marketing the event to sponsors of the symposia and of our plenary lecture and of course managed the registration and promotion of the event. Our PhDs and ECRs have stepped up as volunteer local helpers to ensure everything runs smoothly. It has been a challenge, yet also a deeply rewarding and affirming experience as a result of the supremely collegiate attitudes of everyone involved.
As if that wasn’t enough, we have further cause for celebration, I am to report that Ashley Adamson (HNERC, Newcastle) will deliver the RANK prize lecture.
A more general reflection on symposia, conferences and congresses is that, as scientists, we seek to realise truths, not merely to solve problems. Truth seeking and evidence generation is an enlightened approach, with human good and human knowledge as its goal. Truth and knowledge are achieved through discourse, and ideally through in person discourse and reasoned debate. That is what congress delivers.
Having described a little of the thinking and approach to congress, I’m also reflecting here on why do this at all. At all career stages, it is a rewarding pursuit and can have many positive impacts on your cv and standing:
Leading a conference is a great chance to invite the key thought leaders in your discipline together to and to hear them speak in your own version of a perfect meeting
It will in turn make you visible as a discipline leader in your own right, raising your personal profile with peers and other leaders
Not only this, but it is an excellent way to raise the profile of your centre, research group or research cluster profile with peers and other leaders
If your are canny you can use a workshop report or a meeting report to develop outputs (papers) to consolidate further your standing (a couple of recent examples from HNERC are listed below).
Leading or coordinating a meeting is a great wat to develop management and leadership skills and will give you concrete evidence of this for your cv.
Many societies have funding schemes for small meetings (a great way to make your first steps) including RANK Prize foundation, Nutrition Society, Physiological Society, Biochemical Society.
My suggestion is to start small (not with a congress!), and to focus in your area of interest. Consider a workshop or roundtable with concrete outputs to help focus the event and minds of your delegates.
Some recent meeting outputs from members of our centre:
Oliver M Shannon, Rebecca Townsend, Fiona C Malcomson, Jamie Matu, Alex Griffiths, Amy Jennings, Nicola Ward, Keren Papier, Nicola Best, Chloe French, Pauline Scheelbeek, Curie Kim, Bertha Ochieng, Fareeha Jay, Kaydee Shepherd, Bernard Corfe, Andrea Fairley, Claire T McEvoy, Anne‐Marie Minihane, Yi Jia Sim, Emma Stevenson, Sarah Gregory (2024) Adherence to the Eatwell Guide and population and planetary health: A Rank Prize Forum report Nutrition Bulletin 49: 108-119
Kieran Smith, Anthony W Watson, Marta Lonnie, Wouter M Peeters, Dennis Oonincx, Niki Tsoutsoura, Genis Simon-Miquel, Kamil Szepe, Noriane Cochetel, Alice G Pearson, Oliver C Witard, Andrew M Salter, Malcom Bennett, Bernard M Corfe (2024) Meeting the global protein supply requirements of a growing and ageing population Eur J Nutr 63: 1425-1433
I have always adored food. My parents dubbed me a “foodie” long before I knew what that meant. Trying new foods, cuisines, and ingredients genuinely feeds my soul (pardon the pun) and brings me so much joy. Throughout my studies, cooking after a long library day, whether for myself, friends, or my boyfriend, became my favourite ritual. Those that know me well know that I find cooking extremely therapeutic, it allows me to switch off after a long day and delve into herbs, spices, and new recipes. And yes, hands up, I love snapping an aesthetically pleasing picture of my creations.
I studied and graduated with an MSci degree in Neuroscience from the University of Glasgow and developed a particular passion for population brain health and dementia prevention. I conducted a year-long placement investigating the lifelong risk of dementia in former professional rugby players, as well as contributing to a study investigating the impact of modifiable risk factors for dementia in a cohort of former professional football players.
Following graduation, I worked as a research technician using post-mortem diagnostic techniques to examine the pathological impact of traumatic brain injury on neurodegenerative diseases.
My opponent, Dementia.
I moved to Newcastle to begin my role as a Research Assistant within HNERC, leading the analysis for an Alzheimer’s Research UK-funded project exploring how healthy eating patterns in the UK influence dementia risk.
Briefly, dementia is a disease of the brain that leads to cognitive decline affecting memory, thinking, and everyday functioning. Around 57 million people currently live with dementia worldwide, and this number is expected to rise to ~153 million by 2050. With roughly 10 million new cases each year, the need for action is urgent.
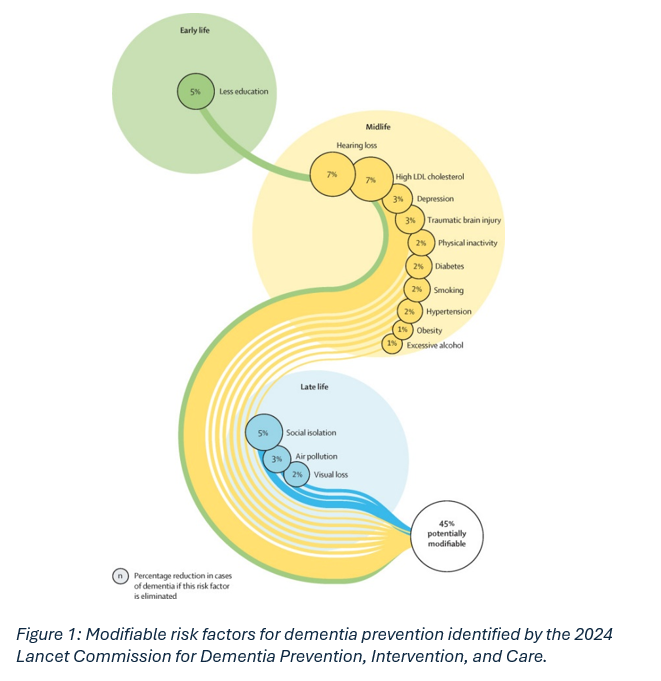
Identifying risk factors for dementia that the population can actively address is essential for disease prevention. Evidence from the 2024 Lancet Commission for Dementia Prevention, Intervention, and Care shows that around 45% of dementia cases could be preventable by addressing modifiable risk factors (Figure 1). Diet is one such risk factor that not only directly, but also indirectly through conditions such as diabetes, hypertension, and obesity, influences dementia risk.
So, what does a brain‑healthy diet look like in the UK?
Most people have heard of the Mediterranean diet. It is widely considered a gold standard dietary pattern for promoting overall and brain health. It emphasises intake of fruits, vegetables, seafood, olive oil, legumes, nuts, and a preference for white over red meat, while limiting sweets, pastries, red meat, and butter, margarine, or cream. Research shows that people who follow this diet tend to have a lower risk of dementia.
However, the Mediterranean diet doesn’t really reflect a typical UK diet. Ingredients can be less accessible or more expensive, and studies show that the Mediterranean diet may actually have weaker associations with health outcomes when applied outside Mediterranean populations.
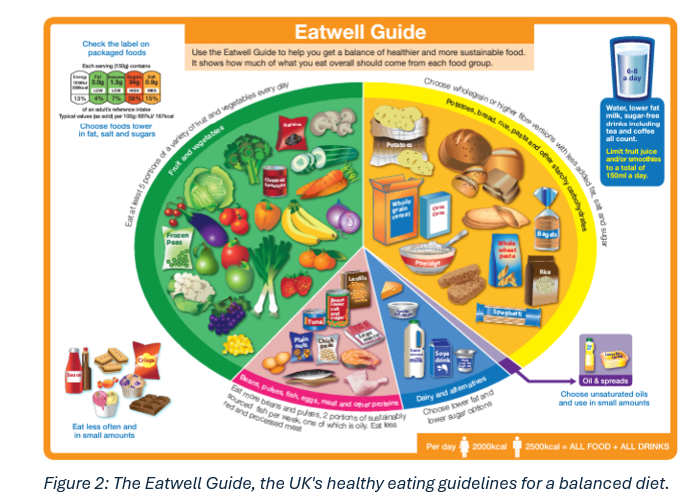
This is where the UK’s own healthy eating model, the Eatwell Guide, comes in (Figure 2). The Eatwell Guide is depicted in a plate‑style diagram showing what a balanced diet looks like based on UK food culture. Like the Mediterranean diet, it encourages a high intake of fruits and vegetables, lean protein sources like seafood and chicken, and limits red/processed meat and high‑fat foods. The Eatwell Guide also promotes consumption of starchy carbohydrates, especially wholegrains, reflecting common UK foods.
Fighting dementia with food.
My team and I are investigating how adherence to the Eatwell Guide may influence dementia risk using the Biobank cohort of over 500,000 participants. Over the past few months, I have been creating dietary scores to measure how closely participants follow the Eatwell Guide. Using these scores, I will then explore whether greater adherence is associated with lower dementia risk, including specific subtypes like Alzheimer’s disease. I will also look at whether the diet–dementia relationship differs across population sub-groups and whether any specific foods or food groups stand out as especially protective.
What Can You Do?
Even if you think you eat “pretty well,” there is always room to improve. When I reflected on my own diet and eating habits, I was surprised by how many easy changes I could make to improve my nutrient intake and in turn improve my overall and brain health.
This project has allowed me to bring my research straight into my kitchen. I have had the joy of creating Eatwell‑aligned recipes to share with our PPI group and discovering new ways to cook the food I already love. I look forward to sharing exciting updates and possibly some new recipes, as this project progresses.
References
Griffiths, A., Malcomson, F., Matu, J., Gregory, S., Fairley, A. M., Townsend, R. F., Jennings, A., Ward, N. A., Ells, L., Stevenson, E., & Shannon, O. M. (2025). Socio-demographic variation in adherence to The Eatwell Guide within the UK Biobank prospective cohort study. https://doi.org/10.1101/2025.06.06.25329110
Livingston, G., Huntley, J., Liu, K. Y., Costafreda, S. G., Selbæk, G., Alladi, S., Ames, D., Banerjee, S., Burns, A., Brayne, C., Fox, N. C., Ferri, C. P., Gitlin, L. N., Howard, R., Kales, H. C., Kivimäki, M., Larson, E. B., Nakasujja, N., Rockwood, K., … Mukadam, N. (2024). Dementia prevention, intervention, and care: 2024 report of the Lancet standing Commission. In The Lancet (Vol. 404, Number 10452, pp. 572–628). Elsevier B.V. https://doi.org/10.1016/S0140-6736(24)01296-0
Shannon, O. M., Ranson, J. M., Gregory, S., Macpherson, H., Milte, C., Lentjes, M., Mulligan, A., McEvoy, C., Griffiths, A., Matu, J., Hill, T. R., Adamson, A., Siervo, M., Minihane, A. M., Muniz-Tererra, G., Ritchie, C., Mathers, J. C., Llewellyn, D. J., & Stevenson, E. (2023). Mediterranean diet adherence is associated with lower dementia risk, independent of genetic predisposition: findings from the UK Biobank prospective cohort study. BMC Medicine, 21(1). https://doi.org/10.1186/s12916-023-02772-3
Stewart, W., Russell, E. R., Lyall, D. M., Mackay, D. F., Cronin, K., Stewart, K., Maclean, J. A., & Pell, J. P. (2024). Health and Lifestyle Factors and Dementia Risk among Former Professional Soccer Players. JAMA Network Open, 7(12). https://doi.org/10.1001/jamanetworkopen.2024.49742
The last few years has seen increasing participation in endurance sporting events such as running half-marathons and marathons and even ultra distance events (Scheer., 2019). However, exercising over such long durations requires a substantial energy demand (ranging between ~4000-11000 kcal for ultra-endurance events; Barrero et al., 2014; Costa et al., 2019 ) and without regular intake of energy via food and fluids it will be harder to maintain the same pace due to depleted energy stores, onset of fatigue ultimately leading to a decline in performance.
At higher exercise intensities (>60% V̇O2max) carbohydrate is the preferred fuel source (van Loon et al., 2001). Whilst we can store carbohydrate in our muscles and liver to help fuel performance, these stores are limited. Sports nutrition research has formed guidelines providing information on carbohydrate dose and sugar type (e.g., glucose and fructose) varying depending on exercise duration (Burke et al., 2011). Exercise durations exceeding 45 minutes it is recommended to consume carbohydrate with doses starting at 30-60 g/h using glucose only to 90 g/h consuming glucose and fructose. For context, a commercially available carbohydrate gel consumes ~30-40g of carbohydrate, meaning to reach the recommended intakes using only carbohydrate gels you would need to be consuming ~2-3 gels every hour. However, there is research in support of using food first approaches, demonstrating that performance is not impacted by choices to eat bananas, raisins, chocolate etc instead of specific sports nutrition products (Reynolds et al., 2022). This can also provide greater variety when fuelling performance to help prevent taste and texture fatigue.
During exercise blood flow is redistributed towards working muscles and away from the gut. This can have negative implications for athletes with approximately 30% of endurance athletes and especially female athletes reporting gastrointestinal symptoms. This is known as Exercise-induced Gastrointestinal Syndrome (EIGS) and includes symptoms such as stomach cramps, nausea and diarrhoea. The ingestion of carbohydrate can exacerbate symptoms, and this can be disastrous for performance and can even contribute to failure to complete endurance events. However, the gut is considered to be a ‘trainable organ’ and regular consumption of carbohydrate during training can help reduce the likelihood of symptoms (Jeukendrup., 2017).
Additional factors to consider include hydration and the external environment. Global warming and climate change mean that most of the world will experience warmer temperatures which is a cause for concern. Dehydration independently of carbohydrate availability can decrease performance so the use of integrated fuel and fluid such as carbohydrate drinks to maintain hydration status and provide fuel, especially in warm conditions. Furthermore, we recently have shown that when exercising in warm conditions we have a greater reliance on the stored carbohydrate within our body even when carbohydrate is provided (Reynolds et al., 2025; Mougin et al., 2025). Meaning that pre and post exercise greater carbohydrate consumption may be required.
References:
Barrero A, Erola P, Bescós R. Energy balance of triathletes during an ultra-endurance event. Nutrients. 2014 Dec 31;7(1):209-22. doi: 10.3390/nu7010209.
Costa RJS, Knechtle B, Tarnopolsky M, Hoffman MD. Nutrition for Ultramarathon Running: Trail, Track, and Road. Int J Sport Nutr Exerc Metab. 2019 Mar 1;29(2):130-140. doi: 10.1123/ijsnem.2018-0255.
Jeukendrup AE. Training the Gut for Athletes. Sports Med. 2017 Mar;47(Suppl 1):101-110. doi: 10.1007/s40279-017-0690-6.
Mougin L, Horner M, Edwards D, Nickels M, Taylor L, James LJ, Mears SA. Heat stress impairs exogenous carbohydrate oxidation during prolonged running when maintaining euhydration. J Appl Physiol (1985). 2025 Dec 1;139(6):1436-1446. doi: 10.1152/japplphysiol.00873.2025.
Reynolds KM, Clifford T, Mears SA, James LJ. A Food First Approach to Carbohydrate Supplementation in Endurance Exercise: A Systematic Review. Int J Sport Nutr Exerc Metab. 2022 Mar 1;32(4):296-310. doi: 10.1123/ijsnem.2021-0261.
Reynolds KM, Funnell MP, Collins AJ, Mears SA, Pugh JN, James LJ. A Warm Environment Reduces Exogenous Glucose Oxidation and Endurance Performance during Cycling with Facing Airflow. Med Sci Sports Exerc. 2025 May 1;57(5):1043-1055. doi: 10.1249/MSS.0000000000003632.
Scheer V. Participation Trends of Ultra Endurance Events. Sports Med Arthrosc Rev. 2019 Mar;27(1):3-7. doi: 10.1097/JSA.0000000000000198.
With winter now in full swing, so too are the ‘winter bugs’ that can cause a number of infections and illnesses, the most common of which being upper respiratory tract infections (URTI) such as cold and flu. Cold and flu are more prevalent during the winter months due to the favourable conditions for these viruses to survive and replicate. While the cold and dry (little moisture/humidity) air during winter is advantageous for pathogens, it is not so great for us or our mucosal immune system (which consists of mucus membranes lining our internal surfaces such as nose, mouth, eyes, lungs etc. that are exposed to the external environment). Cold dry air can lead to the drying of several mucus membranes, causing damage and inflammation to occur.
Add to this, the increased amount of time we spend indoors with other people during winter due to the adverse weather, and it is unsurprising why our risk of illness is significantly higher during winter than other times of the year. Work by my group has shown that the greatest predictor of URTI risk amongst elite athletes was not related to training stressors or wellness indicators, but to household illness. In fact, an athlete’s risk of URTI was increased 3-6 times if a member of their household was ill [1,2]. This finding aligns with broader trends in the general population.
So, how can you reduce your chances of illness this winter?
While the immune system is incredibly complex, there are some straight forward strategies we can implement to give this system the best fighting chance of keeping us healthy this winter. Although the following strategies have been proposed with the immune system in mind [3], many of these will also have beneficial effects on other aspects of our health too (a win-win in my eyes!) and are appropriate for both athletes and the general population.
1. Practicing good hygiene
While not the flashiest strategy to start with, ensuring optimal self-hygiene practices are in place such as washing hands and covering coughs and sneezes (either with a tissue or in the crease of your arm), is key to limiting both the contact and spread of infection, something that COVID-19 highlighted the importance of. Also, avoiding touching areas of your face, such as eyes, nose and mouth (something we tend to do ~9-23 times per hour!) will help to limit self-inoculation/infection.
FACT: Did you know, a sneeze (and its associated nasal droplets) can travel up to ~7-8 m if not covered and stay in the air for ~10 min!
2. Being Physically active & Exercising (with adequate hydration and clothing)
Physical activity and exercise are powerful tools for helping to maintain our immune health. Following the physical activity (PA) guidelines (at least 150 min of moderate-intensity PA throughout the week, or at least 75 min of vigorous-intensity PA) and exercising regularly have consistently been found to reduce our URTI risk, sometimes by as much as 50%. While it is tempting to hibernate during winter, it is still strongly recommended to stay active. When being physically active or exercising outdoors during winter it is important to stay well hydrated, as the cold dry air can not only reduce our drive for thirst but can quickly dehydrate us through increased sweating and fluid loss, which can also lead to damaged mucosal linings. To prevent this from happening it is important to take a drink with you when exercising and to consider wearing clothing that can cover your nose and mouth. There are some great products on the market that do not restrict airflow when covering the face but aid in warming and humidifying the cold dry winter air before reaching the respiratory tract.
3. Prioritising nutrition
A healthy, balanced diet is one of the most effective ways to support your immune health year-round, but it becomes especially crucial during the winter months. Focus on foods rich in vitamins and minerals that help support immune function. Two of my top picks for supporting immune health during winter are Vitamin D and probiotics – both of which have been shown to reduce your URTI risk.
Vitamin D: Since it’s harder to get enough vitamin D from sunlight during the winter, consider incorporating foods like fatty fish (salmon, mackerel), fortified dairy products, and eggs into your diet. If these foods don’t appeal, you could also look to take a Vitamin D3 supplement. Taking around 1000-2000 IU a day during winter is typically advised.
Probiotics: Try incorporating fermented foods like yoghurt, kefir, sourdough and kombucha into your diet this winter. If these foods don’t appeal, you could also look to consume probiotics as a supplement instead. There are various drinks, pills, gummies etc. that are available. Try to look for ones that contain at least 1 billion CFU (colony forming units) and the probiotic strains Lactobacillus and Bifidobacterium.
But what happens if you do catch a URTI such as a cold? Is there anything you can do to limit the illness duration and/or severity?
Even while following the above strategies, it is unrealistic to assume we can completely eliminate the risk of illness this winter. So, is there anything we can do if we end up with a URTI such as the common cold? Thankfully, some of the strategies already discussed (such as probiotic and Vitamin D consumption) can also act to help you better tolerate an illness once infected.
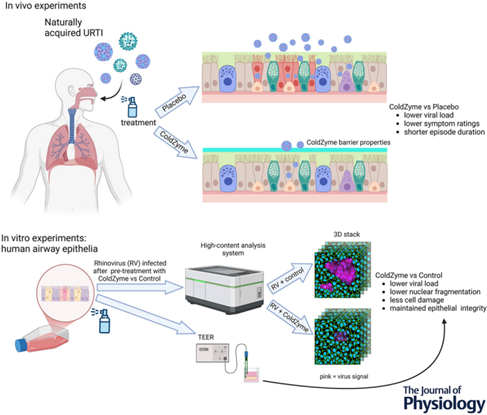
However, are there any over the counter remedies that can help alleviate symptoms of URTI? A recent study I was involved with investigated the use of a commercially available mouth and throat spray (ColdZyme) designed to limit and reduce the symptoms and duration of the common cold. Our group performed both in vivo (monitoring participants over the course of winter to naturally occurring URTI) and in vitro (experimenting on human airway tissue in the lab with rhinovirus) studies using the ColdZyme spray versus a placebo spray [4]. The main findings from this work indicate that ColdZyme spray can reduce both the duration and severity of URTI due to reducing viral load (the amount of virus found in a person’s body fluid), likely due to improved integrity of airway tissue lining and causing less cell damage. As such, this handy travel size mouth and throat spray may be a handy addition to your bag this winter.
Winter doesn’t have to be a season of illness. By adopting a few simple strategies — practising good hygiene, staying active and prioritising nutrition, we can winterproof our immune system and limit our chances of illness.
References
1. Keaney et al., 2021. Household illness is the strongest predictor of upper respiratory tract symptom risk in elite rugby union players. Journal of Science and Medicine in Sport, 24(5), 430-434. doi.org/10.1016/j.jsams.2020.10.011
2. Keaney et al., 2022. Upper respiratory tract symptom risk in elite field hockey players during a dry run for the Tokyo Olympics. European Journal of Sport Science, 22(12), 1827-1835. doi.org/10.1080/17461391.2021.2009041
3. Dulson & Keaney. 2023. Endurance training and athlete immune health. In: I. Mujika (Ed.), Endurance Training – Science and practice. Second Edition (pp. 237-248). Vitoria-Gasteiz, Basque Country: Iñigo MujikaS.L.U. ISBN 978-84-939970-4-5.
4. Davison et al., 2025. ColdZyme reduces viral load and upper respiratory tract infection duration and protects airway epithelia from infection with human rhinoviruses. The Journal of Physiology, 603(6), 1483-1501. doi.org/10.1113/JP288136
Food has always played a big role in my life. Growing up, I had a close relationship with it — I enjoyed exploring new flavours, helping in the kitchen, and discovering how small changes in preparation could completely transform a meal. As a teenager, I began experimenting in the kitchen myself, and my curiosity quickly evolved into a passion.
Choosing Food and Nutrition at A-level felt like a natural step, followed by a degree in Nutritional Sciences. Throughout my early studies, I was fascinated by the science behind food — how cooking transforms nutrients, how dietary needs evolve throughout life, and how what we eat can influence our health over time. Cooking for me has never just been about taste; it’s about understanding what lies behind every meal.
That curiosity led me to research the complex relationship between diet and cancer risk and survival — a topic that continues to inspire me every day. Diet might seem simple, but it’s one of the most powerful, modifiable factors influencing our long-term health.
Exploring diet and cancer risk
During my time at the University of Oxford as a postdoctoral epidemiologist, I worked on large-scale collaborative studies exploring diet and cancer risk, including the Vegetarian Pooling Project. This international collaboration brings together data from more than two million participants across multiple cohorts worldwide to explore how different dietary patterns — such as vegetarian, pescatarian, and meat-eating — relate to site-specific cancer risk.
Our first publication from this work focused on sociodemographic, lifestyle, and health characteristics of participants with different diet groups across the participating cohorts.1 The study highlighted substantial variation between diet groups, underlining the importance of considering these factors when examining links between diet and disease. A second paper, examining diet and cancer risk, is currently under review.
Earlier in my career, I also examined the associations between specific foods and the risk of breast, endometrial, and ovarian cancers in the UK Women’s Cohort Study. The research found that higher intakes of processed and total meat were linked with increased cancer risk, while higher intakes of tomatoes and dried fruit were associated with a lower risk.2
My current research at Newcastle
Now, as a Faculty Fellow at Newcastle University, my work focuses on understanding the relationship between diet and colorectal polyps as part of the COLO-COHORT study — an ongoing project aiming to improve the early detection and prevention of colorectal cancer.
Cancer continues to affect millions of people worldwide and can often appear without warning, profoundly impacting individuals and families. This unpredictability reinforces the importance of identifying modifiable factors — such as diet — that could help prevent cancer or improve outcomes after diagnosis.
In recent years, there has also been growing interest in the gut microbiome — the community of microorganisms living in our intestines — and its potential role in cancer development and prevention. What we eat can influence the composition and function of these microbes, which in turn may affect disease risk.
Alongside my current work, I recently co-authored a systematic review examining the relationship between the faecal microbiome and colorectal neoplasia in shotgun metagenomic studies.3 The review highlighted consistent alterations in microbial composition between individuals with colorectal neoplasia and healthy controls, supporting growing evidence that the gut microbiome may play a role in early detection and prevention. This work complements my ongoing research in COLO-COHORT, where we are exploring how dietary factors might interact with the gut microbiome to influence colorectal polyp risk.
I’m also developing grant and fellowship proposals to further explore how diet might influence colorectal cancer survival, an area that remains under-researched but holds great potential for improving patient outcomes. Through this research, I hope to contribute to clearer, evidence-based guidance on how everyday dietary choices can help prevent cancer or improve outcomes after diagnosis.
Away from my desk
Outside of research, I still find joy in food — especially in trying new recipes and sharing meals with friends and family. It’s my creative outlet and a reminder of why I do what I do: because food connects us all, shapes our health, and continues to fascinate me just as much as it did when I first stepped into a kitchen.
References
Dunneram, Y. et al. (2024). Methods and participant characteristics in the Cancer Risk in Vegetarians Consortium: a cross-sectional analysis across 11 prospective studies. BMC Public Health, 24(1):2095. https://doi.org/10.1186/s12889-024-19209-y
Dunneram, Y. et al. (2019). Diet and risk of breast, endometrial and ovarian cancer: UK Women’s Cohort Study. British Journal of Nutrition, 122(5):564-574. https://doi.org/10.1017/S0007114518003665
Manning, S. et al. (2025). Systematic Review: The Relationship Between the Faecal Microbiome and Colorectal Neoplasia in Shotgun Metagenomic Studies. Alimentary pharmacology & therapeutics, 62(6):568-584. https://doi.org/10.1111/apt.70252
People with Type 1 diabetes (T1D) have a pancreas that no longer secrets enough insulin, so from diagnosis they are dependent on insulin being administered in either an injection or via an insulin pump. This means people must manually balance and adjust their insulin medication according to their meals, while also accounting for what the sugar concentration in the blood is. Unfortunately, life can be a daily battle and tightrope walk to keep their blood sugar in the healthy range and preventing it from going too high (damages blood vessels, eyes, kidneys, nerves), or too low, which can be dangerous for the brain’s energy supply.
Exercise can be a dilemma for people with Type 1 diabetes
In general, people with T1D are encouraged to be physically active due to the associated health benefits (e.g. better heart and lung system), and in general the disease doesn’t hold people back, with thousands running marathons yearly, there is a T1D professional cycling team, there are stars like Henry Slade and Sir Steve Redgrave who reached the pinnacle of their sports (Figure 1). However, for many people exercise is avoided due to worries of their diabetes control deteriorating, or exercise causing dangerously low blood sugar, termed hypoglycaemia (fuel to the brain is compromised). Hypoglycaemia can be fatal if not treated, and the more frequent this event occurs, the more accustomed the body becomes to it and the usual feelings we get when the brains sugar is getting too low (pale, hunger, pins and needles, confusion), don’t occur. This results in a dangerous situation where brain fuel is compromised, but the defence symptoms against it are blunted. Naturally, exercise potentially leading to increased occurrence of hypoglycemia is an understandable barrier.
Figure 1: Type 1 diabetes athletes. Professional cycling team Team Novo Nordisk and England Rugby union international, Henry Slade.
“If I exercise my diabetes gets worse” versus “exercise is no problem for me”
For decades, in clinic observations have reported a wide range in how people cope with frequent exercise with clinicians observing improvements in some and a deterioration of diabetes control in others. Indeed, some clinical colleagues remained sceptical on recommending people engaged in exercise at all, such was the risk that their diabetes control would worsen. Over the past 10 years our group has sought to understand why this is, with the aim that more targeted and personalised support can be created for the individual.
Are the insulin producing cells in the pancreas truly destroyed?
It has been recently shown that while people are dependent on insulin as medication, the pancreas may have an underlying and persistent ability to produce small amounts of insulin still. This is important, because any remaining pancreas function could play a role in how the person walks that tight rope when exercising.
We recently conducted a study where we measured how much ‘C-peptide’ people were secreting in their blood and urine in response to food. C-peptide is released from the pancreas along with insulin and is used to assess how much function or damage is present in the pancreas. We found that in people with established Type 1 diabetes (>5 years), that there was a wide range in how much C-peptide people produced. Some had zero levels of C-peptide, while others had very small amounts and a small fraction of people were still producing a significant amount. We then took these groups of people and got them to walk on an incline treadmill for 45 minutes and monitored their blood sugar for a couple of days after exercise. We found in those with no C-peptide their diabetes control got worse, while in those who were positive, their diabetes control improved. So, despite having the disease similar amounts of time, being of similar fitness, and similar overall diabetes control, a controlled bout of exercise resulted in a divergent split in their blood sugar control; those with C-peptide improving, and those negative, getting worse (1, 2).
Age at diagnosis as an indirect measure of pancreas function
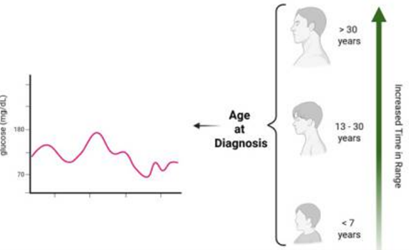
We sought to understand the exercise tightrope further by looking at how the age at someone’s T1D diagnosis might impact their blood sugar control when exercising. Analysing insulin producing cells from pancreas donors shows that the damage in the pancreas seems to be different depending on when they were diagnosed, early childhood versus teenage versus adulthood. We explored how splitting people by these diagnosis-age categories impacted their diabetes control. We showed that those diagnosed before the age of 13 had worse diabetes control when exercising, and those with adulthood diagnosis had better blood sugar when exercising (Figure 2). Put simply, two people of the same fitness, overall diabetes control, and the same duration of diabetes, but one diagnosed as a toddler versus one diagnosed in adulthood, could have divergent changes in their diabetes control when doing the same bout of exercise (3).
Figure 2: Adapted from Taylor et al. (3) – Age at Type 1 diabetes diagnosis versus time in normal blood glucose range.
What does this mean for the exercise tightrope?
We hope our data will provide evidence to clinicians to monitor every person’s C-peptide levels, regardless of how long they have had T1D. This could provide useful information in identifying people at risk of finding exercise hard, it could also mean pushing others to more challenging diabetes control targets. There are also tools like diabetes technology, blood sugar sensors, and exercise education programmes that could be used in a more targeted way to support people to exercise without compromising their diabetes control. At a personal level, people can suffer from a lot of anxiety and distress because of how hard they find managing their diabetes, while others find things easier. If the clinical team are aware that there could be some underlying disease differences that explain this – ultimately, this will improve the persons understanding of their own disease, and potentially make safe exercise, with targeted support, adoptable into the lives of all people with Type 1 diabetes.
References
Taylor GS., Shaw, AC., Smith, K., Wason, J., McDonald, TJ., Oram, RA., Stevenson, E., Shaw, JAM., West, DJ. (2020). Capturing the real-world benefit of residual beta-cell function during clinically important time-periods in established type 1 diabetes. Diabetic Medicine, 39:e14814
Taylor, GS., Smith, K., Capper, TE., Scragg, JH., Bashir, A., Flatt, A., Stevenson, EJ., McDonald, TJ., Oram, RA., Shaw, JA. & West, DJ. (2020). Post-exercise glycemic control in type 1 diabetes is associated with residual β-cell function. Diabetes Care, 43(10), 2362-2370.
Taylor, GS., Bruger, B., Scragg, JH., Page, O., Schmid, H., Nsengimana, J., West, DJ. & Shaw, JA. (2025). Impact of Age at diagnosis and insulin delivery modality on free-living glycemia in Type 1 diabetes during periods associated with dysglycemia: a retrospective analysis of the type 1 diabetes exercise initiative study. Diabetes Technology & Therapeutics, in press.
Whilst physical activity has long been promoted as cure for different ailments, our understanding of, and interest in, just how far-reaching those effects are has grown in the last few decades. One of the benefits of a physically active lifestyle is that at higher intensities it leads to higher physical fitness. Having a fitter heart and lungs means that they can supply your muscles with energy and oxygen more efficiently, so you can keep an activity going for longer. Building stronger muscles also helps strengthen bones, preventing fractures (and making carrying shopping or children easier!). Physical fitness also helps maintain a healthy body composition and reduces the risk of cardiovascular disease and Type 2 diabetes. In addition to the physical benefits, and there is also good evidence suggesting that being physically fit benefits children and young people’s mental wellbeing, too.
What I’m trying to get across is the need not just to increase the amount of physical activity everyone does, but also to make sure that it is enough to increase their fitness.
Sadly we know that globally, children and young people’s physical fitness is in decline, so we need to find innovative ways of encouraging children and young people to get active. Key to this is accessibility – we need to remove any barriers, whether financial, physical, social or geographical – and offer fun, challenging, varied activities, that children and young people want to join in with.
There are multiple ways to address the problem, including safe active transport, free sports, convenient locations, access to appropriate kit, and exercise sessions at school. High intensity exercise can increase fitness in adolescents, but so far has been led by researchers or teachers. We wanted to increase the sustainability of the programme by using older peers to lead the exercises for younger pupils, which had not previously been tested.
In 2023 I ran a small pilot study to test whether we could train sixth form students (aged 17-18 years) to lead Year 7 pupils (aged 11-12 years) in high intensity exercise sessions, twice a week. We had designed the study with pupils and teachers, to try and offer them what they wanted, and get as many pupils as possible taking part. This wasn’t just for the ‘sporty’ kids – we wanted everyone to join in and feel the benefits. Most children and young people are in school, so this is an easy place for them to take part. The sessions were only 10 minutes long, and took place during morning tutor time. All the exercises could be done in school uniform, and exercises were chosen based on what the pupils said they wanted to do.
Over an afternoon of training with my collaborator Dr Katy Weston (University of Strathclyde) and me, the Young Leaders were taught safe and effective exercises, and how to demonstrate them. They were given a training manual and access to an online site with all the information. For 8 weeks, the five Young Leaders got to know the Year 7 pupils in the group, and led their sessions. The exercises changed from full-body exercises like squat jumps to boxing with sprints, an activity the Year 7s really enjoyed doing.
I was at each of the sessions to support the Young Leaders, and was able to observe the changes in both them and the younger pupils. The confidence and organisational skills of the Young Leaders grew as time went on, and it was great to see the bonds forming between the Year 7s and the Young Leaders. The Year 7s were enthusiastic about joining in each time, and gave it their all. The Young Leaders were dedicated to their role, and tried to involve all the pupils in each session. In addition, we had positive comments from teachers and both sets of pupils, and lots of helpful suggestions on improvements we could make to the training. The benefits to the pupils that were entirely separate from any improvements to their fitness were really encouraging, so we are working on the next version of the programme to test with another group of young people.
We are currently writing up the study for publication (watch this space!), but this is something we will be championing for years to come!
With thanks to my collaborators Dr Katy Weston (University of Strathclyde), Dr Brook Galna (Murdoch University) and Dr Naomi Burn (University of South Australia), and the pupils and teachers at Dukes Secondary School.
References:
Demchenko, I. et al., (2025). British Journal of Sports Medicine: bjsports-2024-109184.
Lubans, D. et al., (2021). British Journal of Sports Medicine 55:751-758.
Weston K et al., (2016). PLOS ONE 11(8): e0159116.